Breaking New Ground in Hypertension Management: Clinical Trial Evaluates Non-Invasive Ear Nerve Stimulation for Drug-Resistant High Blood Pressure

The landscape of cardiovascular medicine may be on the cusp of a subtle yet profound transformation following the release of recent data from a pioneering clinical trial evaluating a non-invasive medical device designed to treat stubborn high blood pressure. Spearheaded by distinguished researchers at Queen Mary University of London, the novel therapeutic intervention utilizes gentle electrical pulses delivered directly through the external ear to target the autonomic nervous system. Published in Hypertension, a prestigious peer-reviewed journal of the American Heart Association, the SCRATCH-HTN trial evaluated the safety, tolerability, and practical application of this technology when administered by patients within the comfort of their own homes. While the primary endpoint—a generalized reduction in blood pressure across all trial participants compared to a placebo—did not reach statistical significance, secondary and subgroup analyses revealed highly encouraging signals. Specifically, patients who entered the study with more severe, treatment-resistant hypertension demonstrated notable and clinically relevant reductions in their blood pressure readings when exposed to active neuromodulation. These findings suggest that while the technology may not offer a universal fix for every hypertensive patient, it could eventually serve as a targeted, accessible therapeutic adjunct for individuals whose conditions defy conventional pharmaceutical interventions. As cardiovascular disease remains a leading global cause of morbidity and mortality, the medical community is closely watching how non-invasive neuromodulation evolves in subsequent, larger-scale investigations.
Chronology and Background of the SCRATCH-HTN Trial
The journey toward evaluating transcutaneous autonomic neuromodulation (tAN) for hypertension has been decades in the making, rooted in a growing understanding of how the nervous system dictates cardiovascular dynamics. The autonomic nervous system acts as the body’s internal control center, involuntarily regulating heart rate, vascular resistance, and blood pressure. In chronic hypertension—often referred to as the silent killer—this system frequently becomes hyperactive, signaling blood vessels to constrict and the heart to pump with increased force, thereby driving blood pressure persistently upward. Traditional medical management relies heavily on lifestyle modifications, such as dietary sodium restriction and increased physical activity, alongside a vast pharmacopeia of antihypertensive medications, including ACE inhibitors, calcium channel blockers, and diuretics. Despite these diverse pharmacological arsenals, a significant percentage of patients fall into the category of having uncontrolled or resistant hypertension. Their blood pressure stubbornly remains above target thresholds despite adherence to multi-drug regimens.
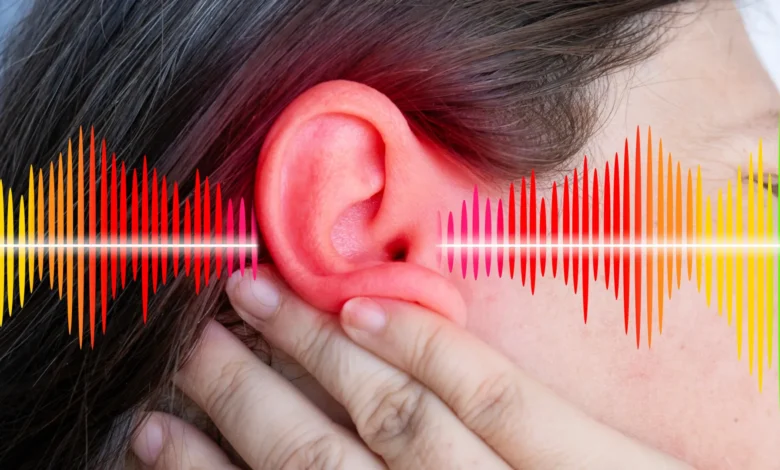
Recognizing this clinical bottleneck, biomedical engineers and clinicians sought alternatives that could modulate autonomic output without resorting to invasive surgical procedures, such as renal denervation. This quest led to the development of the investigational device by Afferent Medical Solutions. The hardware design is deceptively simple: a handheld generator connected to dual clips engineered to attach securely to the tragus, the small, prominent piece of cartilage situated immediately in front of the ear canal. The tragus is uniquely suited for this purpose because it is densely innervated by the auricular branch of the vagus nerve, a primary component of the parasympathetic nervous system capable of influencing cardiovascular tone.
The SCRATCH-HTN trial was formally structured to test this mechanism in a controlled environment. Funded primarily by the National Institute for Health and Care Research (NIHR), the trial enrolled 63 carefully selected participants across clinical sites. All enrolled individuals suffered from uncontrolled hypertension, meaning their clinical readings consistently breached safe medical thresholds despite ongoing treatment with at least one anti-hypertensive medication. The methodology was rigorously designed as a randomized, double-blind, sham-controlled trial—the gold standard in clinical research. Participants were randomly segregated into two distinct cohorts: one group received active electrical stimulation designed to modulate autonomic nerve traffic, while the control group received a sham treatment using an identical device programmed to deliver negligible or imperceptible current. This meticulous blinding ensured that any observed psychological or physiological changes attributable merely to the act of using a device could be effectively isolated from the true pharmacological or bioelectric effect of the treatment.
Detailed Examination of Trial Methodology and Patient Compliance
The operational protocol of the SCRATCH-HTN trial was structured not only to measure physiological efficacy but also to gauge the pragmatic viability of home-based bioelectric therapies. Modern chronic disease management increasingly emphasizes patient empowerment and decentralized care, reducing the burden on overburdened healthcare infrastructures like the UK’s National Health Service (NHS).
During the initial phase of the trial, participants were instructed to apply the device clips to their tragus for a duration of 30 minutes daily over a rigorous two-week induction period. Following this intensive phase, the treatment burden was tapered down to a maintenance schedule of once weekly for the subsequent ten weeks, culminating in a 12-week total evaluation window. Throughout this period, researchers closely monitored adherence rates, patient comfort, and potential adverse events.
The compliance data yielded exceptionally positive insights. The vast majority of participants successfully adhered to the prescribed schedule, navigating the mechanics of self-administration without professional clinical supervision. Furthermore, the safety profile of the device proved immaculate. The electrical pulses were described as gentle and well-tolerated, with minimal to no reported side effects, skin irritation, or discomfort. This high level of patient acceptability is a critical metric in chronic disease research; even the most efficacious therapy fails if patients find it too cumbersome, painful, or inconvenient to incorporate into their daily lives.
However, when the data from the entire unselected study population were aggregated and analyzed at the conclusion of the trial, the primary endpoint fell short of statistical significance. The overall cohort receiving active neural stimulation did not experience a statistically meaningful drop in blood pressure when compared directly against the sham-device control group. For the casual observer, this finding might signal a failed trial. Yet, in advanced clinical research, broad population analyses frequently mask nuanced, highly valuable signals hidden within specific patient phenotypes—a reality that prompted the research team to turn their attention toward prespecified subgroup analyses.
Subgroup Analysis Unveils Promising Signals in Severe Hypertension
In clinical trial design, prespecified subgroup analyses are statistical evaluations planned before any data are unmasked, safeguarding against the intellectual trap of data dredging or p-hacking. True to this methodological rigor, the Queen Mary University research team had outlined plans to examine subsets of the trial population based on baseline disease severity.
When investigators isolated the data pertaining to participants who entered the trial with more severe, entrenched forms of hypertension, a striking divergence emerged. Unlike the broader, heterogeneous cohort, these high-severity patients exhibited a clear, measurable reduction in blood pressure when subjected to active electrical stimulation compared to their counterparts in the sham group. This subset analysis fundamentally shifts the narrative of the SCRATCH-HTN trial from a generalized setback to a targeted discovery.
It stands to reason from a pathophysiological standpoint that individuals with markedly elevated, treatment-resistant hypertension possess a higher baseline of autonomic dysfunction—specifically, an overactive sympathetic nervous system drive—that makes them far more responsive to vagal nerve stimulation. Conversely, patients with milder or more labile hypertension may have blood pressure elevations driven by entirely different physiological mechanisms, such as arterial stiffness, fluid retention, or endocrine disorders, which would remain largely unresponsive to auricular neuromodulation.
This nuanced outcome highlights the evolving paradigm of precision medicine. Modern therapeutics are increasingly moving away from the blunt instrument of "one-size-fits-all" population treatments toward highly tailored interventions designed for specific patient endophenotypes. If validated, transcutaneous autonomic neuromodulation could become a bespoke clinical tool reserved precisely for those hard-to-treat patients who have exhausted traditional pharmaceutical options or suffered from severe medication side effects.
Expert Perspectives and Institutional Reactions
The academic and clinical communities have responded to the publication of the SCRATCH-HTN trial with a mixture of cautious optimism and scientific rigor. As the first rigorous, randomized, sham-controlled study of its kind to evaluate this specific transcutaneous neuromodulation technology in a home setting, the trial establishes an essential baseline for future device-based cardiovascular research.
Dr. Ajay Gupta, the study’s Chief Investigator, Clinical Reader at Queen Mary University of London, and a respected Consultant Physician at Barts Health NHS Trust, articulated the significance of the findings during post-publication media briefings. Dr. Gupta emphasized both the innovative nature of the technology and the pragmatic promise it holds for global healthcare systems.
"This is an exciting, highly patient-acceptable technology that could ultimately provide a cheap, scalable solution for millions," Dr. Gupta stated. He further contextualized the dual nature of the results, noting, "Although the trial did not achieve significance across the broad unselected group, those with more severe hypertension exhibited a clear blood pressure reduction in the active group compared to sham. As the first and most thorough study of its kind, this points towards important new research directions that could help us understand whether non-invasive neuromodulation can benefit particular groups of patients with uncontrolled hypertension."
Other cardiologists and independent researchers not directly involved in the trial have echoed these sentiments, noting that while the preliminary data are insufficient to prompt immediate clinical guideline changes, they successfully justify the mobilization of larger, adequately powered phase III clinical trials. These independent experts emphasize that the absence of adverse events is a massive victory for early-stage bioelectronic medicine, proving that external neuromodulation can be safely deployed into the community without posing systemic safety risks to vulnerable cardiac patients.
Broader Implications for Cardiovascular Health and Bioelectronic Medicine
To fully grasp the potential societal impact of this research, it is necessary to examine the staggering global burden of hypertension. High blood pressure is universally recognized as the single most significant risk factor for cardiovascular disease, serving as a primary underlying catalyst for ischemic heart disease, myocardial infarctions (heart attacks), cerebrovascular accidents (strokes), and chronic kidney disease. The physiological mechanism is relentless: chronically elevated pressure within the arterial tree places continuous mechanical stress on the endothelium—the delicate inner lining of blood vessels—accelerating the formation of atherosclerotic plaques and increasing the workload on the left ventricle of the heart, ultimately culminating in cardiac hypertrophy and heart failure.
Despite the widespread availability of inexpensive generic antihypertensive medications, global blood pressure control rates remain dismally low. Contributing factors include patient non-adherence driven by multi-pill fatigue and intolerable side effects, clinical inertia among primary care providers, and treatment-resistant hypertension where physiological pathways override pharmaceutical interventions. The economic toll is equally staggering, costing healthcare systems billions of dollars annually in emergency department visits, inpatient hospitalizations, and long-term disability care.
In this context, the emergence of bioelectronic medicine represents a tantalizing frontier. Bioelectronics—often referred to as electroceuticals—seeks to replace or supplement traditional chemical drugs with targeted electrical signals that modulate the body’s native neural circuits. Unlike small-molecule drugs, which circulate systemically and frequently cause off-target side effects (such as electrolyte imbalances, dizziness, or fatigue), neural stimulation can theoretically be localized, dialed down, or paused instantly.
The fact that the device tested in the SCRATCH-HTN trial is non-invasive distinguishes it sharply from previous bioelectronic breakthroughs, such as vagus nerve stimulation devices that required surgical implantation of electrodes around the vagus nerve in the neck, or invasive catheter-based renal denervation procedures performed in specialized catheterization laboratories. A non-invasive, clip-on ear device carries virtually zero surgical risk, requires no anesthesia, can be prescribed by a general practitioner, and is entirely managed by the patient at home. If future clinical trials confirm its efficacy in severe hypertension, the cost-effectiveness and scalability of such a device could revolutionize outpatient chronic disease management, offering a viable third pillar of treatment alongside lifestyle changes and pharmacology.
Next Steps and the Path to Clinical Adoption
Despite the enthusiasm surrounding the SCRATCH-HTN trial, the scientific method demands rigorous replication before any experimental therapy transitions from a research curiosity to an approved clinical standard. The investigative team at Queen Mary University of London, alongside their funding partners and commercial developers, are already looking toward the horizon to design the next generation of studies.
Future clinical trials must address several critical variables that remained unanswered in the initial exploratory study. First, researchers must conduct larger, statistically powered trials specifically targeting populations with severe, drug-resistant hypertension. By focusing the inclusion criteria exclusively on this phenotype, investigators can definitively test the hypothesis generated by the SCRATCH-HTN subgroup analysis.
Second, optimal dosing schedules require refinement. The SCRATCH-HTN trial utilized a 30-minute daily regimen tapering to weekly sessions over 12 weeks, but whether this represents the optimal therapeutic frequency remains unknown. Dose-ranging studies will be essential to determine if longer stimulation durations, different electrical frequencies, or varied pulse widths yield superior or more durable reductions in blood pressure.
Third, researchers need to investigate the durability of the treatment effect. Does the blood pressure-lowering benefit persist long-term with continued use, or does the autonomic nervous system eventually accommodate or habituate to the electrical stimulus, rendering it ineffective over multi-year timeframes? Long-term registry studies tracking patients over months and years will be critical to answering this question.
Finally, economic evaluations and health technology assessments will be necessary to determine cost-effectiveness. While the manufacturing costs of a handheld electrical stimulator are theoretically low compared to chronic drug expenditures or surgical interventions, reimbursement models within national healthcare systems and private insurance networks must be established to ensure equitable patient access.
Conclusion
The publication of the SCRATCH-HTN trial in Hypertension marks a fascinating and potentially pivotal chapter in the ongoing evolution of cardiovascular therapeutics. While the trial did not achieve its primary objective of demonstrating a universal reduction in blood pressure across an unselected hypertensive population, its deeper findings offer a compelling glimpse into the future of precision medicine. By demonstrating that non-invasive, home-administered electrical stimulation of the ear’s neural pathways is exceptionally safe, well-tolerated, and capable of significantly reducing blood pressure in patients with severe, hard-to-control hypertension, the Queen Mary University researchers have opened a promising new avenue of scientific inquiry. As the medical community awaits the larger, confirmatory trials necessary to validate these subgroup findings, the intersection of bioelectronics and cardiology inches closer to delivering a practical, patient-friendly solution for millions of individuals struggling against the relentless tide of uncontrolled high blood pressure.
Related posts: